Stress Fracture in the Foot: Signs, Rest, and Return to Running
How stress fractures in the foot develop, how to tell one apart from other overuse pain, and how to rebuild bone and tissue capacity for a safe return to running.
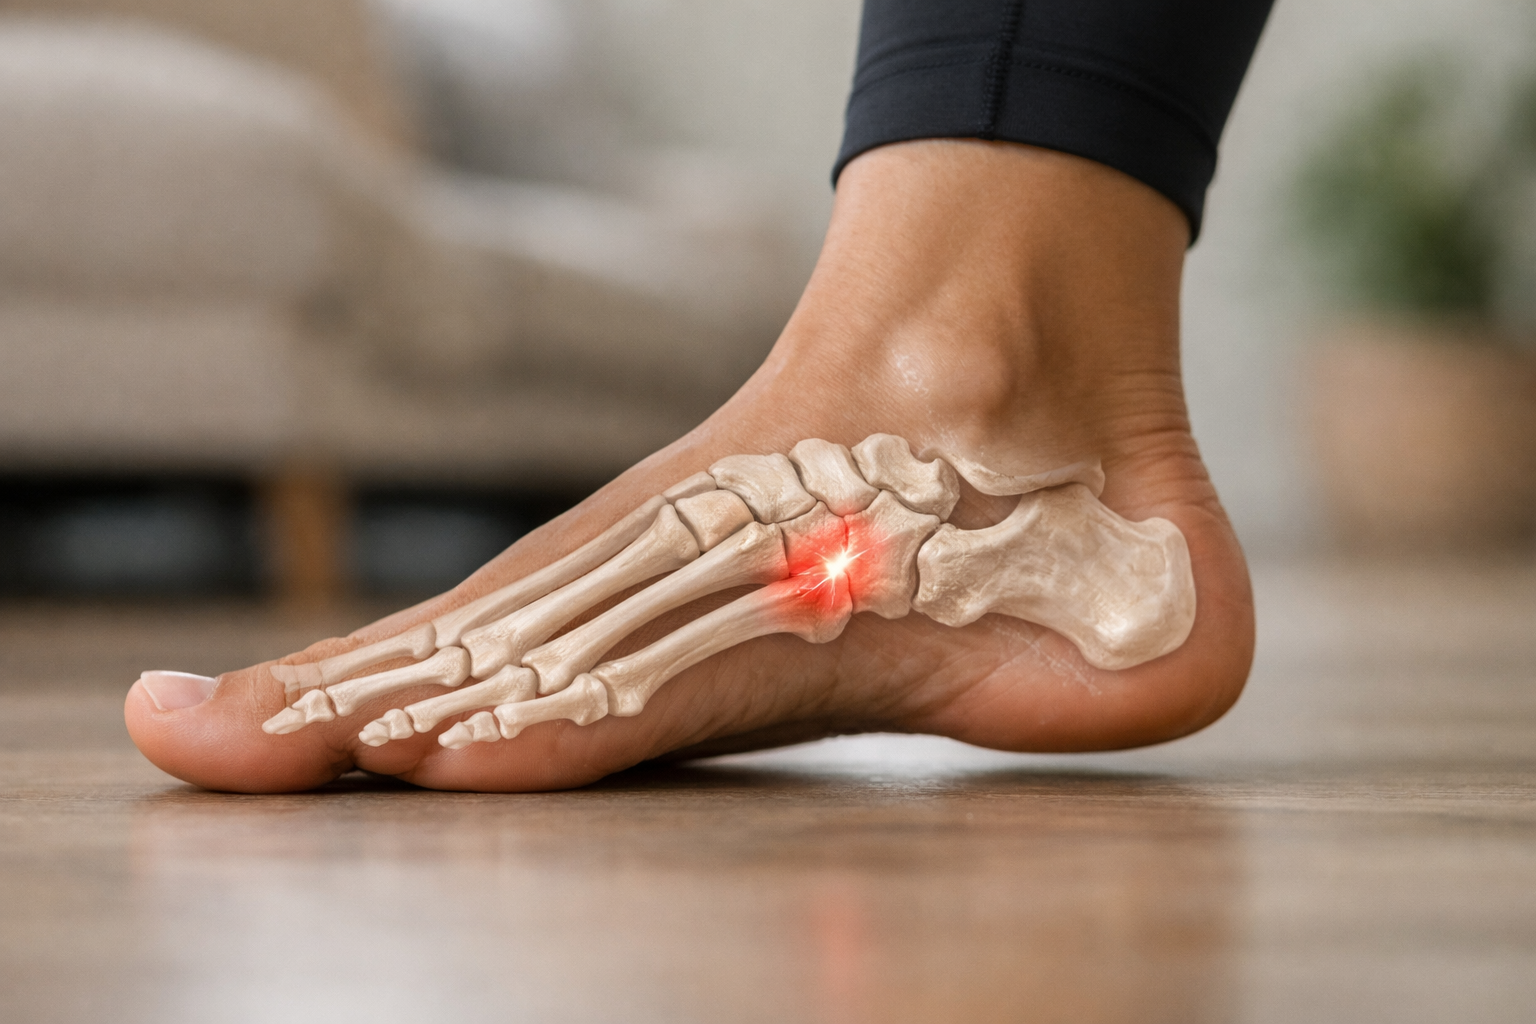
What a Stress Fracture Actually Is
A stress fracture is a small crack in bone that develops from repeated load the bone hasn’t yet built the capacity to handle. It’s not usually the result of one bad step. It’s the result of many steps, days, and weeks where the demand on the bone outpaced its ability to repair and remodel in response.
Bone is living tissue. It responds to load by remodeling, breaking down slightly and rebuilding stronger, over and over. When training volume, intensity, or surface changes faster than bone can adapt, the breakdown side of that equation gets ahead of the rebuild side. Keep that up long enough and you get a stress reaction, then a stress fracture if the load doesn’t change.
This is the same load-versus-capacity problem we talk about with plantar fasciopathy and Achilles overuse, just applied to bone instead of soft tissue. The tissue isn’t broken because it’s weak. It’s injured because the demand outran what it could currently tolerate.
What Are Four Signs of a Stress Fracture?
The classic pattern most clinicians look for:
- Pinpoint pain over a specific spot on the bone, rather than a diffuse ache across the whole foot.
- Pain that worsens with impact activity (running, jumping, even brisk walking) and eases with rest.
- Pain that shows up earlier in the activity over time. What used to hurt at mile four starts hurting at mile one.
- Swelling or tenderness to the touch directly over the bone, sometimes without much visible bruising.
A lot of runners also notice the pain becomes present with simple daily walking, not just running, as the stress reaction progresses. That shift, pain moving from “only during hard training” to “during normal walking,” is worth paying attention to.
How Do I Know If I Have a Stress Fracture in My Foot?
You can’t diagnose it with certainty at home, but a pattern that includes localized bone pain, a recent increase in mileage or intensity, and pain that gets worse with continued impact is enough reason to get it looked at. The metatarsals (especially the second and third) and the navicular bone are common sites in runners, largely because of how load transfers through the midfoot with each stride.
This can be consistent with a stress fracture, but heel and forefoot pain can come from several other sources too. Plantar fasciopathy, metatarsalgia, nerve irritation, and tendon overuse can all produce pain in similar areas. An evaluation is what actually sorts out which one you’re dealing with, rather than guessing from symptoms alone.
Can I Test for Foot Stress Fractures at Home?
There’s a rough field test some clinicians and athletes use called the hop test: standing on the affected foot and hopping. Sharp, localized pain that reproduces the injury is a reasonable signal something needs evaluation. It is not a diagnostic tool, and a negative hop test doesn’t rule anything out. Don’t rely on it to decide whether to keep training.
How Do You Test for a Stress Fracture?
In the clinic, this usually starts with a history and a physical exam, checking for point tenderness, swelling, and pain with specific loading tests. Imaging often follows:
- X-rays are usually the first step, but early stress fractures frequently don’t show up on X-ray for two to three weeks, because the bone changes are too subtle yet.
- MRI is more sensitive and can pick up a stress reaction before it becomes a visible fracture line, which is why it’s often used when symptoms are strong but X-rays look clean.
- Bone scans are used less often now but can help in unclear cases.
Can Urgent Care Find a Stress Fracture?
Urgent care can order an X-ray and rule out an acute fracture, which is useful if there was a fall or a sudden traumatic onset. But because early stress fractures often don’t appear on X-ray, a clean urgent care X-ray doesn’t mean you’re in the clear. If pain persists despite a normal X-ray, follow-up with a physician or physical therapist who can consider MRI or a longer-term plan is reasonable.
What Can Be Mistaken for a Foot Stress Fracture?
Several conditions overlap with stress fracture symptoms:
- Plantar fasciopathy, which usually produces pain at the heel rather than the midfoot, and is worse with first steps in the morning.
- Metatarsalgia, a general overload of the ball of the foot, without an actual bone crack.
- Morton’s neuroma, which causes burning or tingling between the toes.
- Tendon overuse (posterior tibial, peroneal), which produces pain along the tendon path rather than a single point on bone.
- Soft tissue bruising or contusion from a direct impact.
Because these conditions are managed differently, and because continuing to run on an actual stress fracture can make it worse, getting an accurate diagnosis matters more here than with most foot complaints.
Should You Walk on a Stress Fracture?
This depends on the bone involved and how it’s responding, which is part of why self-diagnosis and self-treatment are risky here. Some stress fractures (many metatarsal fractures, for instance) tolerate protected walking reasonably well. Others, particularly in the navicular or fifth metatarsal, are known for poor blood supply and higher risk of complications if they’re loaded through normal walking. Those often need a period of significantly reduced weight-bearing, sometimes in a boot, sometimes with crutches, decided by imaging and clinical judgment rather than how it feels day to day.
This is a case where “stay as active as tolerable” needs a more cautious interpretation than usual. Total rest for weeks on end is rarely the answer for most musculoskeletal pain, but true stress fractures, especially high-risk ones, are one of the situations where a period of real load restriction protects the outcome. Your clinician’s guidance on weight-bearing status should take priority over general activity advice.
How Do You Treat a Stress Fracture? What Will a Doctor Do?

Treatment generally follows a staged approach:
- Offload the bone. Depending on location and severity, this might mean a walking boot, activity modification, or in some cases non-weight-bearing for a period.
- Address contributing factors. A sudden jump in mileage, a change in running surface, worn-out shoes, or low energy availability (not eating enough to support training load) are common contributors. Bone density and hormonal factors are sometimes relevant too, particularly in athletes with a history of amenorrhea or disordered eating patterns.
- Confirm healing before reloading. Follow-up imaging or a clinical reassessment (pain-free with hopping, palpation, and daily activity) is often used before restarting impact activity.
- Rebuild capacity gradually. Once cleared, running volume comes back in stages, not all at once. This is the same progressive-loading principle that applies to tendons and fascia: start below the level that provokes symptoms, hold there long enough for the tissue to adapt, then step up.
A physical therapist’s role in this process often includes addressing the mechanical factors that contributed in the first place: cadence, footwear, hip and calf strength, and training structure, so the bone that healed doesn’t get re-injured the same way.
Can I Tape My Foot for a Stress Fracture?
Taping can provide some symptomatic support and proprioceptive feedback, but it doesn’t offload bone the way a boot does, and it won’t accelerate healing. It’s reasonable as a minor comfort measure during controlled activity once a clinician has cleared you to move that way, but it isn’t a substitute for appropriate weight-bearing restrictions during the acute phase.
Can a Foot Stress Fracture Heal on Its Own?
Many do, given appropriate offloading and time. Bone has a strong capacity to heal when the load causing the problem is removed. But “on its own” still typically means weeks of reduced impact activity, sometimes in a boot, not just powering through with mild modifications. Trying to run through a stress fracture, or returning too soon because pain has faded, is one of the more reliable ways to turn a several-week injury into a several-month one.
What Happens If You Don’t Treat a Foot Stress Fracture?
Continuing to load an unhealed stress fracture risks the crack progressing to a complete fracture, which is a substantially bigger problem, sometimes requiring surgery, especially in high-risk locations like the navicular or the base of the fifth metatarsal. Delayed healing, chronic pain, and a much longer return to running are the realistic downsides of ignoring persistent, localized bone pain in a runner.
Getting Back to Running

Once a clinician has confirmed the bone is ready to reload, the return to running should be graded, not immediate. A typical approach starts with walking, progresses to a run-walk protocol, and gradually increases continuous running time and distance over roughly six to twelve weeks, with the exact pace depending on the fracture site, your training history, and how the tissue responds along the way.
A useful general guideline during this phase: keep pain at or below about a 4 out of 10 during and after activity, and if soreness from a session hasn’t settled within about 24 hours, that’s a sign the last increase was too much, not that something has gone wrong structurally. Symptoms can lag a day or two behind the load that caused them, so judge your progression by the pattern over several days, not by how any single run felt in the moment.
Strengthening the muscles that support the arch and absorb shock, calves, hip abductors, and intrinsic foot muscles, is part of reducing the odds of a repeat injury. Our article on foot strengthening exercises walks through a progressive approach to building that capacity.
When to See Someone
Persistent, localized foot pain that doesn’t improve with a few days of reduced activity, pain that’s present with simple walking, or foot pain following a noticeable jump in training volume all warrant an evaluation. Stress fractures respond well to appropriate management for many people, but the earlier they’re caught, the shorter and more predictable the recovery tends to be. If you’re dealing with foot pain that isn’t clearly explained or isn’t responding the way you’d expect, a physical therapist or physician can help sort out what’s actually going on and build a plan around it.