How Serious Is a High Ankle Sprain? Recovery and Return to Running
A high ankle sprain is slower and more demanding than a rolled ankle because the injured structures get loaded every time you push off. Here's what actually drives the timeline, how to read your own response, and what a real return to running looks like.
Most people who ask how serious a high ankle sprain is are asking something more specific underneath. They want to know whether this is the kind of injury that quietly costs them a season. Whether they are going to end up with a permanently unreliable ankle. Whether they should be worried that four weeks in, it still hurts to push off.
So let’s answer that directly. A high ankle sprain is usually more demanding than a standard rolled ankle, and it typically takes longer. That is not the same as dangerous. Most are managed without surgery, and many people return to full running and sport. The reason it feels alarming is that the recovery curve is different in a way nobody warns you about: early progress can be reasonable, and then you hit a phase where walking feels fine but pushing off, cutting, and running still don’t.
That phase is where people panic. It’s also where most of the real work happens.
Why This Injury Behaves Differently
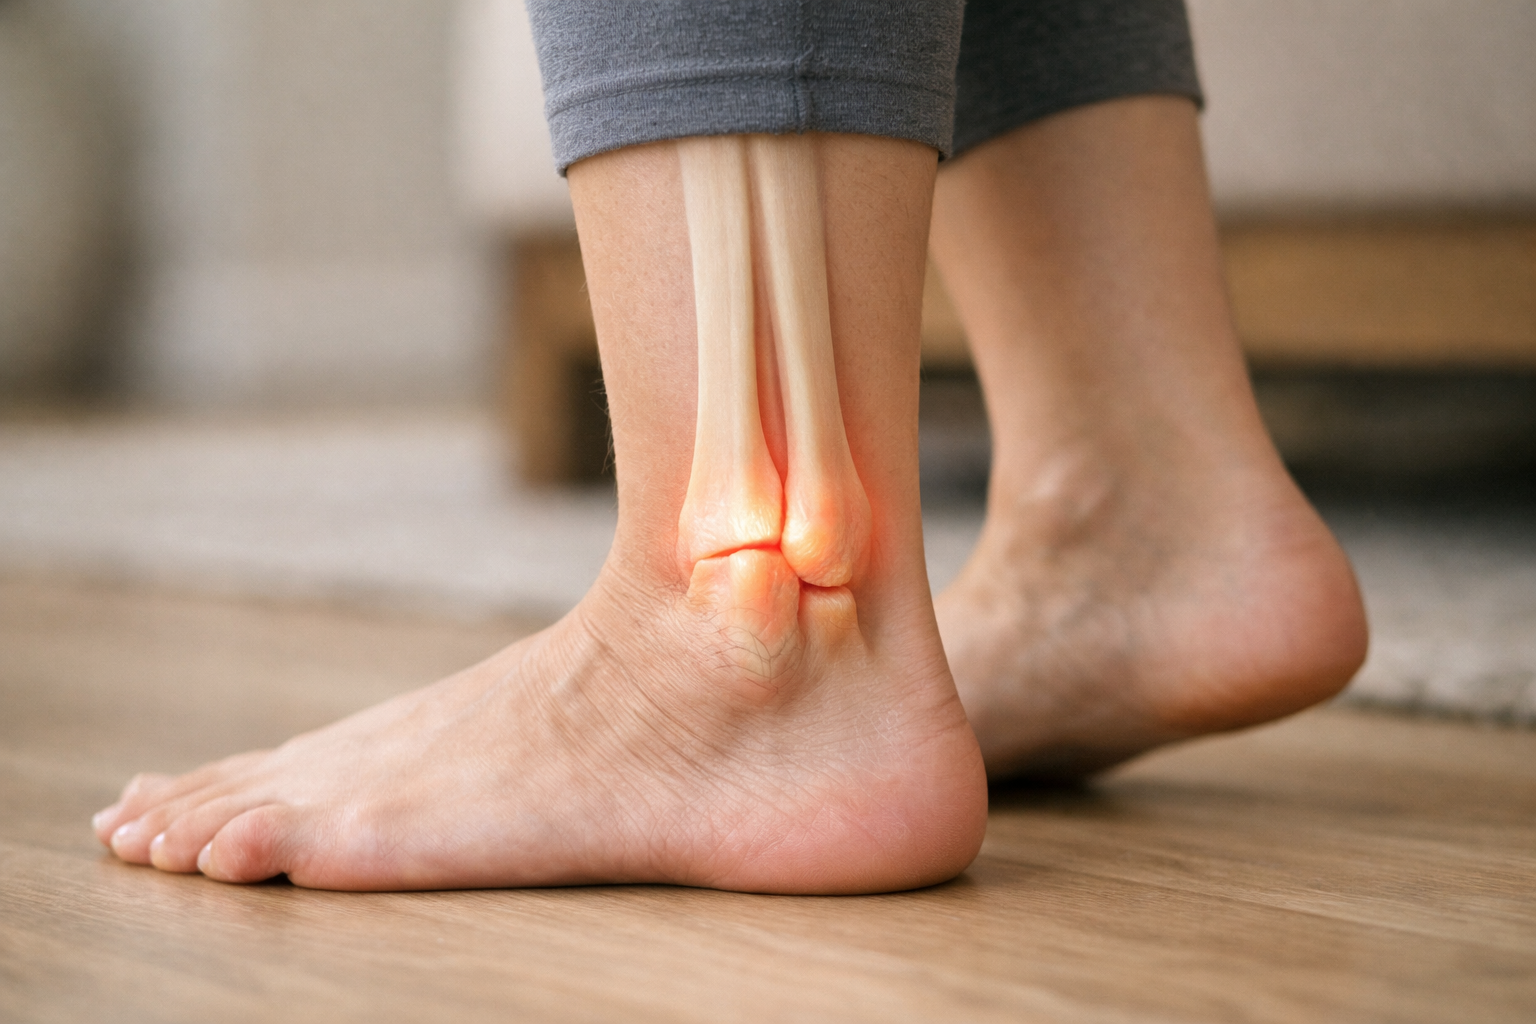
The common ankle sprain involves the ligaments on the outside of the ankle, below the bony bump. A high ankle sprain involves the structures that hold your two lower leg bones, the tibia and fibula, snug together just above the joint. That connection is called the syndesmosis.
Here’s why that matters functionally. Every time your foot flexes upward and your body passes over it, the talus bone wedges slightly between those two leg bones and pushes them apart a fraction of a millimeter. When the syndesmosis is healthy, it resists that and you never notice. When it’s injured, that same motion is exactly what provokes it.
Walking on flat ground pushes that position mildly. Pushing off to run pushes it hard. Cutting, decelerating, and going uphill push it harder still. So an ankle can feel genuinely okay walking across a parking lot and still be nowhere near ready to jog, and this is not the injury faking you out. The demand is different.
One more piece: the syndesmosis is under load in a rotational sense too. High ankle sprains commonly happen when the foot is planted and the body rotates over it, which is why they show up in football, soccer, hockey, skiing, and wrestling more than in the casual step-off-a-curb roll.
(If you’re still sorting out which injury you actually have, the companion article on this site, “High Ankle Sprain vs. Regular Ankle Sprain,” walks through the differences in more detail. This one assumes you’re past that question and want to know what recovery actually involves.)
What’s the Worst Kind of Ankle Sprain?
If we’re ranking by how long people are typically sidelined and how much rehab is involved, syndesmotic (high) sprains generally sit at the top of the non-fracture list. A grade 3 lateral sprain can be very painful and very swollen, but the outside ligaments are loaded less directly by straight-ahead running, and people often progress faster than the swelling would suggest.
The high ankle sprain is different because the injured tissue sits right in the path of force transmission between your leg and your foot. You cannot really unload it and still walk normally.
The worst-case version is a high ankle sprain with actual separation between the tibia and fibula, sometimes alongside a fracture. That subset is the one where surgery enters the conversation, usually to hold the two bones in the right relationship while things heal. That’s a minority of cases. Most are managed conservatively with a period of protection followed by a structured rebuild.
What Does a Grade 3 Ankle Sprain Look Like?
Grade 3 means a complete tear of the involved ligament or ligaments. In practical terms, people often describe:
- Significant swelling, often appearing quickly rather than over hours
- Bruising that can spread up the leg or down into the foot over several days
- Real difficulty or inability to put weight through the leg
- A feeling of the ankle giving way or feeling loose when weight does go through it
- Pain that doesn’t settle much with elevation and rest in the first day or two
With a high ankle sprain specifically, the tenderness tends to sit above the joint line, along the front of the ankle where the two leg bones meet, and sometimes further up the shin. Squeezing the calf mid-shin can reproduce pain down at the ankle, which is not typical of a garden-variety rolled ankle.
This can be consistent with a more significant injury, but grading from the outside is genuinely unreliable. Swelling is a poor proxy for tissue damage. Plenty of dramatic-looking ankles turn out to be moderate injuries, and some quiet-looking ones turn out to involve more. That’s what examination and, when indicated, imaging are for.
When to Worry About a High Ankle Sprain
Most of the time, the answer to “should I be worried” is no, you need a plan more than you need worry. But there are situations that warrant getting looked at promptly rather than waiting it out:
- You can’t bear weight at all, or you can only take a few steps, in the first day or two after the injury.
- Bone tenderness directly over the bony bumps on either side of the ankle, or over the outer leg bone higher up. Fractures travel with high ankle sprains more often than people realize.
- The ankle feels unstable or shifty under load, like it’s going to slide out from under you.
- Numbness, tingling, or a cold or pale foot. Swelling can press on structures, and this is worth same-day attention.
- Severe swelling with pain that keeps escalating rather than easing over the first 48 to 72 hours, especially if the foot feels tight and hard.
- You’re three or four weeks out and nothing has changed. Not worse, just no meaningful progress in what you can do. Plateaus that early usually mean something was missed or the loading plan needs adjusting.
The common failure mode with this injury isn’t people ignoring an emergency. It’s people treating a syndesmotic injury like a routine sprain, doing two weeks of ice and rest, going back to sport when walking feels normal, and then reinjuring it. The gap is rarely the initial care. It’s the absence of a plan for the middle part.
Is It Okay to Walk on a High Ankle Sprain?
Usually yes, in some form, and often sooner than people expect. But the version of walking matters.
In the early phase, many people are given a boot or a brace. The purpose isn’t to prevent all movement forever. It’s to limit the specific motion that stresses the healing syndesmosis, mainly the upward flex of the ankle combined with rotation, while still letting you get up and move. Being upright and loading the leg supports circulation, keeps the calf and hip from deconditioning, and keeps the nervous system from getting weirdly protective about the whole limb.
What’s genuinely counterproductive is either extreme. Total rest until pain is gone tends to produce an ankle that is calm and completely unprepared. Pushing through a limp because you’ve decided you’re tough tends to produce a flare and a compensation pattern that outlives the injury.
A workable standard for the early weeks: walk in whatever protection you’ve been given, at whatever distance lets you walk with a reasonably normal rhythm, and keep the pain at or under roughly a 4 out of 10 during and after. For a lot of people that threshold works well as a guide, not a rule. Then check how the ankle feels the next morning. If it settled back to baseline within about a day, that amount was appropriate. If it was still angrier 24 hours later, it was a bit much, and you scale back and build again.
That back-and-forth is the actual method. Do something reasonable, watch the response, adjust. The calendar gives you rough structure. The response tells you what comes next.
How Long Will a High Ankle Sprain Hurt?
Honest answer: longer than a regular sprain, and the pain changes character as you go rather than simply fading.
A rough pattern many people follow, with the strong caveat that grade, age, prior injuries, and the demands you’re returning to all shift this:
- Week 1 to 2: Pain at rest, pain with weight-bearing, swelling, stiffness. The sharpest phase.
- Week 2 to 6: Rest pain largely settles. Walking improves, sometimes a lot. What persists is pain with specific positions, particularly flexing the ankle deeply, going up stairs, or pushing off.
- Week 6 onward: Day-to-day life feels mostly fine. Higher-demand movements still provoke something. This is the stage people find most confusing, because they feel recovered and aren’t performing like it.
Milder syndesmotic injuries sometimes resolve in a matter of weeks. More significant ones can take a few months before running and cutting feel genuinely solid, and surgical cases longer. “Several months” is not a sign that something went wrong. It’s a common course for this particular injury.
Some mild soreness after new activity can persist well into the return-to-running phase. That’s not the same as damage. Pain is information about what the tissue was ready for on a given day, not a report of fresh injury. Learning to read it that way makes the whole process much less frightening.
What’s the Worst Day of a Sprained Ankle?
For most people it’s day two or three, not the day it happened. Adrenaline blunts things initially, swelling accumulates over 24 to 72 hours, and the ankle gets stiff and tight as fluid fills the joint capsule. Then you sleep, the leg is horizontal all night, and the first steps in the morning are miserable.
That morning stiffness is a sensitivity pattern, not overnight deterioration. Tissue that has been still for hours is less tolerant of the first load it meets. It typically eases as you move. This is worth knowing because those first steps convince a lot of people they went backward when they didn’t.
What Is the Fastest Way to Heal a High Ankle Sprain?
There’s no shortcut that beats biology. But there’s a large difference between a well-run recovery and a passive one, and it mostly comes down to three things.
Protect early, but briefly. Reduce the motions that stress the healing tissue for the period it needs, then start giving it work. Protection is a phase, not a treatment plan. Held too long, it costs you calf strength, ankle motion, and balance, and you spend weeks buying back what you gave away.
Keep the rest of the body working. Your hip, your core, your other leg, your aerobic fitness. Cycling, pool work, upper-body training, single-leg work on the uninjured side. None of that heals the ligament directly. All of it means that when the ankle is ready, you’re not starting from zero everywhere else.
Then load it, progressively and on purpose. This is the part that gets skipped. Ligament and the surrounding tissues adapt to mechanical stress. Not to rest, not to ice, not to stretching alone. Gentle, controlled loading in the ranges the ankle tolerates, then more range, then more force, then speed, then direction changes. Early improvements come fast because your nervous system gets better at recruiting muscle. The actual structural adaptation happens over a longer stretch, often something like 8 to 12 weeks of consistent work for many people, and sometimes longer for this injury.
That lag is exactly why returning as soon as the pain stops is a trap. Pain is an early indicator. Capacity catches up later.
What generally helps around the edges: managing swelling in the first days, moving within comfort, getting the calf and the whole lower leg strong, sleeping and eating like someone who is healing. What doesn’t seem to change the underlying timeline: any single passive treatment used on its own, in place of progressive loading.
Should I Wrap My Sprained Ankle Overnight?
Generally, no need. Compression is most useful in the first few days for swelling control while you’re upright and moving around. Overnight, your leg is horizontal, so gravity is already doing the job compression would do.
More practically, a wrap applied at bedtime and forgotten can end up too tight as swelling shifts, and you can’t feel it happening while asleep. If you want elevation overnight, a pillow under the lower leg is simpler and safer. If someone treating you specifically asked you to sleep in a brace or boot for stability reasons, follow that. That’s a different purpose than compression.
Will My Ankle Sprain Heal on Its Own?
The tissue will heal. Bodies do that. The question is what it heals into.
Left entirely alone, a high ankle sprain often ends up with an ankle that walks fine and doesn’t quite trust itself. Reduced ability to flex the ankle forward, a calf that never got its strength back, balance that is subtly worse on that side, and a pattern of avoiding full push-off that you stop noticing but that shows up in the next injury, sometimes somewhere else entirely.
There’s also a more specific concern with this injury. If the tibia and fibula aren’t sitting in the right relationship, the ankle joint mechanics change, and over years that can matter. That’s part of why an actual evaluation is worth it even for an injury you’re confident about.
So: healing happens on its own. Capacity doesn’t. Recovery is built, and the building is the part that determines whether you get back to what you were doing or settle for a version of it.
Returning to Running After a High Ankle Sprain

This is where the high ankle sprain earns its reputation, because running loads the syndesmosis in the exact way it doesn’t want to be loaded early on.
Before running, most people need to be able to do a few things comfortably. Not perfectly. Comfortably.
- Walk normally at speed without limping, for a duration well beyond what you’d run at first.
- Flex the ankle forward well. Knee-to-wall, heel down: you want something close to the other side. Restricted forward flex means every stride borrows motion from somewhere else.
- Calf strength that shows up under load. Single-leg heel raises, through full range, enough repetitions that the calf actually fatigues, both straight-knee and bent-knee versions.
- Hop and land on one leg without pain and without the ankle wobbling to catch you.
- Handle the previous day’s work. If yesterday’s session leaves the ankle worse today, you’re not ready to add running on top.
When you do start, treat it as loading, not as fitness. Short intervals of easy jogging with walking between, on flat, predictable ground. Straight lines only at first. The pattern most people do well with is running every other day at the start, using the off day as information: if the ankle settles within roughly 24 hours, the dose was reasonable and you can build a little. If it’s still stirred up, you hold or step back.
Then you add, one variable at a time. More total time. Then a bit more pace. Then uneven ground, then gentle turns, then hills (which demand more forward ankle flex, so they often provoke this injury more than flat running does). Then, for field and court athletes, cutting and deceleration, which are the true test of the syndesmosis and belong at the end of the progression rather than as a quick check before returning.
A thing worth saying plainly: your total load is cumulative. The run isn’t the only thing your ankle did that day. Standing at work, walking the dog, a day of travel, a concrete floor, a long grocery trip. When a flare shows up, look at the whole day, not just the workout. And symptoms often lag a day or two behind the thing that caused them, so the culprit isn’t always the most recent activity.
When a Flare Happens

It will, somewhere in there. A run that felt fine, and the next morning the ankle is stiff and sore again.
That’s not the injury returning. It’s feedback that the load exceeded what the ankle could handle that day. You back off a level, let it settle, and rebuild from a slightly lower point. The trend over weeks is what matters, and the trend almost never moves in a straight line.
The things worth watching are different: swelling that returns and stays, a sense of the ankle giving way, pain that climbs rather than settling over several days, or new pain in a different place. Those are worth a conversation with a clinician rather than a self-adjustment.
What Progress Actually Looks Like
People judge this injury almost entirely by pain, and that’s an incomplete measure. Ask different questions:
- Are you walking farther before it complains?
- Does it settle faster after activity than it did two weeks ago?
- Are the mornings less stiff, or stiff for a shorter time?
- Can you do things this week you couldn’t do last week?
- Is the pain lower for the same activity, even if it’s not zero?
Any of those improving is real progress, even on a day when the pain number hasn’t moved. Function matters as much as pain, and with an injury this slow, function usually improves first and gives you evidence that the pain will follow.
A Note on Getting It Looked At
If your ankle isn’t clearly improving, if you can’t put weight on it, if it feels unstable, or if pain is escalating rather than settling, get evaluated. Fractures travel with these injuries. Separation between the leg bones changes the management. And not every pain above the ankle is a syndesmotic sprain, so an exam that sorts out what’s actually going on is worth more than a guess, however well-researched.
Beyond the acute stuff, the most common reason people stay stuck with this injury isn’t a missed diagnosis. It’s that nobody handed them a plan for the middle, the weeks between “it doesn’t hurt to walk” and “I trust it at full speed.” That stretch is where the ankle either gets rebuilt or quietly doesn’t. It’s also the part that responds best to someone watching how your ankle answers each step up and adjusting from there.